Health · Cancer Screening · Clinical Guidelines
American Cancer Society Recommends Regular PSA Screening in Major Guideline Change
The first overhaul since 2010 moves from discussion-only advice to a direct testing schedule, while adding steps meant to reduce unnecessary biopsies and treatment.
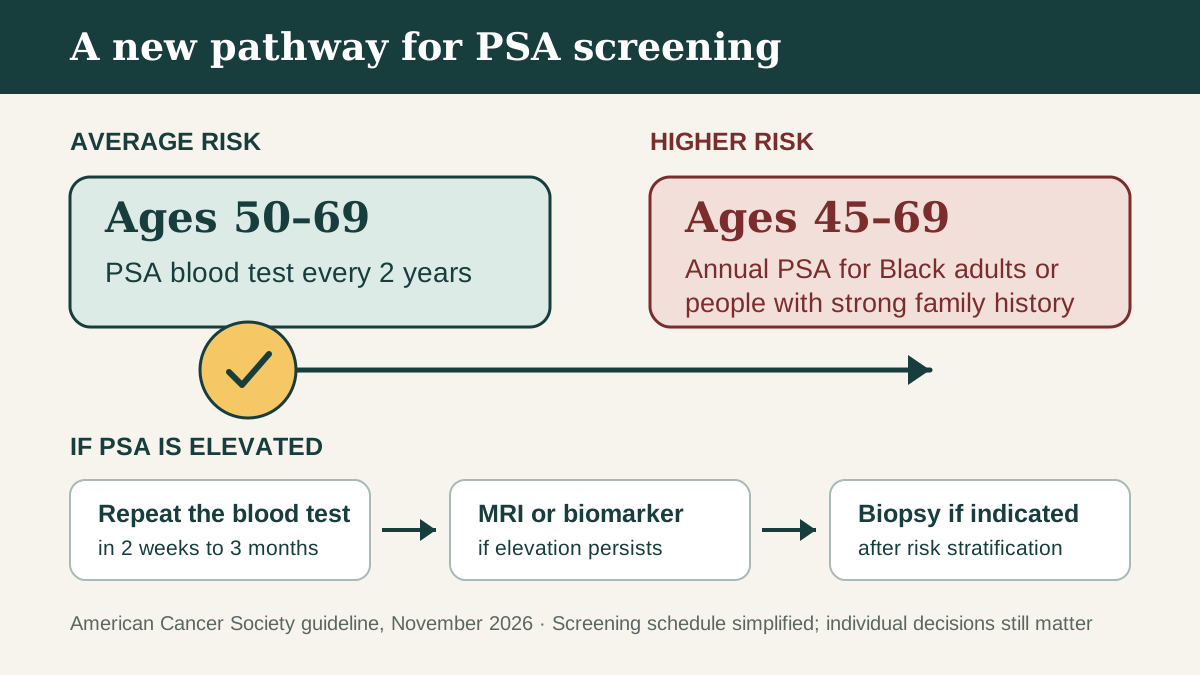
Verified baseline: regular testing replaces discussion-only advice
The American Cancer Society’s new guideline recommends a prostate-specific antigen blood test every two years from ages 50 through 69 for people at average risk of prostate cancer. Black adults and people with a strong family history should begin at 45 and be screened annually through 69.
That is a substantive change from the society’s 2010 position, which told people to make an individual decision after discussing benefits and harms with a clinician but did not directly recommend regular screening. The evidence review and full recommendations were published in CA: A Cancer Journal for Clinicians.
The guideline uses the term “men” because it is based on studies organized by sex. Its screening questions can also apply to transgender women and nonbinary people who have a prostate. Individual anatomy, prior prostate treatment, medicines and health history can change how a clinician interprets PSA.
Who the new schedule covers
| Group | ACS schedule | Important boundary |
|---|---|---|
| Average risk | Every two years, ages 50–69 | Information about benefits and harms should come before testing |
| Black adults or people with a strong family history | Every year, ages 45–69 | Strong history means a first-degree relative diagnosed before 65 or multiple first-degree relatives |
| One first-degree relative diagnosed at 65 or older | Every two years, ages 45–69 | Risk differs from the stronger family-history category |
| Ages 70–74 | Individual decision | Balance of benefit and harm is uncertain |
| Ages 75–79 | Generally no routine screening | Some very healthy people with rising prior PSA may reasonably consider it |
| Age 80+, or life expectancy under 10 years | Do not screen | Delayed benefits are unlikely to outweigh near-term harms |
The society estimates 333,830 U.S. prostate-cancer diagnoses and 36,320 deaths in 2026. It gives earlier and more frequent advice for Black adults because incidence and mortality are substantially higher in that population. Those are group-level risk differences, not a diagnosis for any individual.
An elevated PSA is not a cancer diagnosis
PSA is produced by normal as well as cancerous prostate cells. Benign enlargement, inflammation and temporary factors can raise the result. The new pathway therefore recommends repeating an elevated test after two weeks to three months before moving to invasive follow-up. The society uses 3.0 nanograms per milliliter as the elevation threshold for ages 45–69 and 6.5 for ages 70–74.
If the elevation persists, the guideline recommends a prostate MRI and/or a validated biomarker test to help decide whether biopsy is warranted. It does not recommend a digital rectal exam as a screening test. For a low-risk cancer found after this process, active surveillance—structured monitoring instead of immediate surgery or radiation—should be the initial management option for many patients.
Why the benefits and harms are still debated
PSA screening can find aggressive cancer before symptoms or spread, when treatment may be more effective. It can also detect slow-growing tumors that would never cause illness. False-positive results can lead to anxiety, imaging and biopsy; treatment of an overdiagnosed cancer can cause urinary incontinence, erectile dysfunction and other lasting effects.
The Cancer Society says newer evidence and better risk-stratification tools have shifted that balance toward regular screening for the defined age groups. The protective steps are part of the recommendation, not optional details: confirm a result, use MRI or biomarkers when appropriate, reserve biopsy for higher-risk cases and favor surveillance for low-risk disease.
This is a clinical guideline, not a mandate. The current U.S. Preventive Services Task Force recommendation, issued in 2018 and now under review, says ages 55–69 should make an individual decision and recommends against screening at 70 or older. The American Urological Association advises a baseline PSA from 45–50 for average risk and 40–45 for elevated risk, followed by personalized intervals.
What the change means for appointments and coverage
Someone within the new age and risk groups can ask a primary-care clinician whether PSA screening belongs in the next preventive visit, what interval fits prior results and what confirmation would happen after an elevation. Symptoms such as difficulty urinating, blood in urine or semen, persistent bone pain or unexplained weight loss are not “screening” questions and warrant clinical evaluation on their own timetable.
Insurance rules do not automatically change when a nonprofit medical group updates a guideline. Medicare Part B covers a PSA blood test once every 12 months for eligible beneficiaries age 50 or older; other plans can have different eligibility, cost-sharing and network rules. A clinician or insurer can explain coverage before testing. This article provides general information, not personalized medical advice.
Fact, analysis, forecast and opinion
Verified fact: the Cancer Society now directly recommends regular PSA screening for defined age and risk groups, plus repeat testing and risk stratification before biopsy. Analysis: the change is as much about managing the consequences of a positive test as expanding access to the first test. Forecast: clinicians and health plans may revise reminders and preventive-care workflows, but adoption and coverage will vary and the federal task force has not yet issued its update. Opinion: Health Politics Daily takes no position on whether any individual should be screened; that judgment belongs to an informed patient-clinician decision using the person’s risk, health and preferences.
Bias Lens: a medical-evidence dispute, not a partisan contest
Verified baseline: the American Cancer Society changed its own guideline after a new evidence review. It did not change federal policy, establish a cancer diagnosis from one PSA result or prove that every screened person benefits.
Primary source — American Cancer Society: foregrounds the screening schedule, disparities and a multi-step follow-up pathway. Broad public-service reporting — Associated Press: centers what middle-aged patients need to know and explains why past PSA use produced overtreatment. Health-business reporting — Reuters: emphasizes the evidence shift, the projected disease burden and medical advances that may reduce harms.
A left-center-right comparison is not meaningful for this story: the consequential difference is among clinical organizations’ age ranges and evidence judgments, not partisan ideology. Naming ideological outlets simply to fill three boxes would create false symmetry. The useful comparison is the Cancer Society’s new schedule against the federal task force and urology guidance.
What remains uncertain
The federal task force’s pending update could narrow or widen the gap among U.S. guidelines. The Cancer Society’s models and evidence synthesis support a population recommendation, but real-world outcomes will depend on who gets tested, access to MRI and specialists, whether repeat testing happens before biopsy, and whether low-risk cancers are monitored instead of treated.
It also remains uncertain whether earlier annual screening will reduce the large mortality disparity for Black adults without creating disproportionate false positives and invasive follow-up. The guideline offers a pathway; health systems will determine whether all of its safeguards are available equitably.
Our earlier guide to interpreting a cancer-trial headline explains why early evidence is not the same as a treatment decision. Our coverage of India’s cancer-drug price controls examines how a health-policy change can still leave access questions unresolved.
Principal sources
- American Cancer Society — updated screening guideline
- CA: A Cancer Journal for Clinicians — evidence-based guideline
- U.S. Preventive Services Task Force — current recommendation and update status
- American Urological Association — early-detection guideline
- Associated Press — patient-focused explanation and historical context
- Reuters — disease burden, risk differences and guideline rationale
No suitable directly relevant official or publisher-authorized video with clear, persistent embedding permission was available, so no video was embedded.
Discussion
Reader comments
Discuss the reporting, not other readers. Claims should be sourced; threats, harassment, misinformation, medical misinformation and personal data are removed.
Comments are publicly visible after automated and editorial review. Guest comments are stored on this device until submitted; account details are governed by our Privacy Policy.